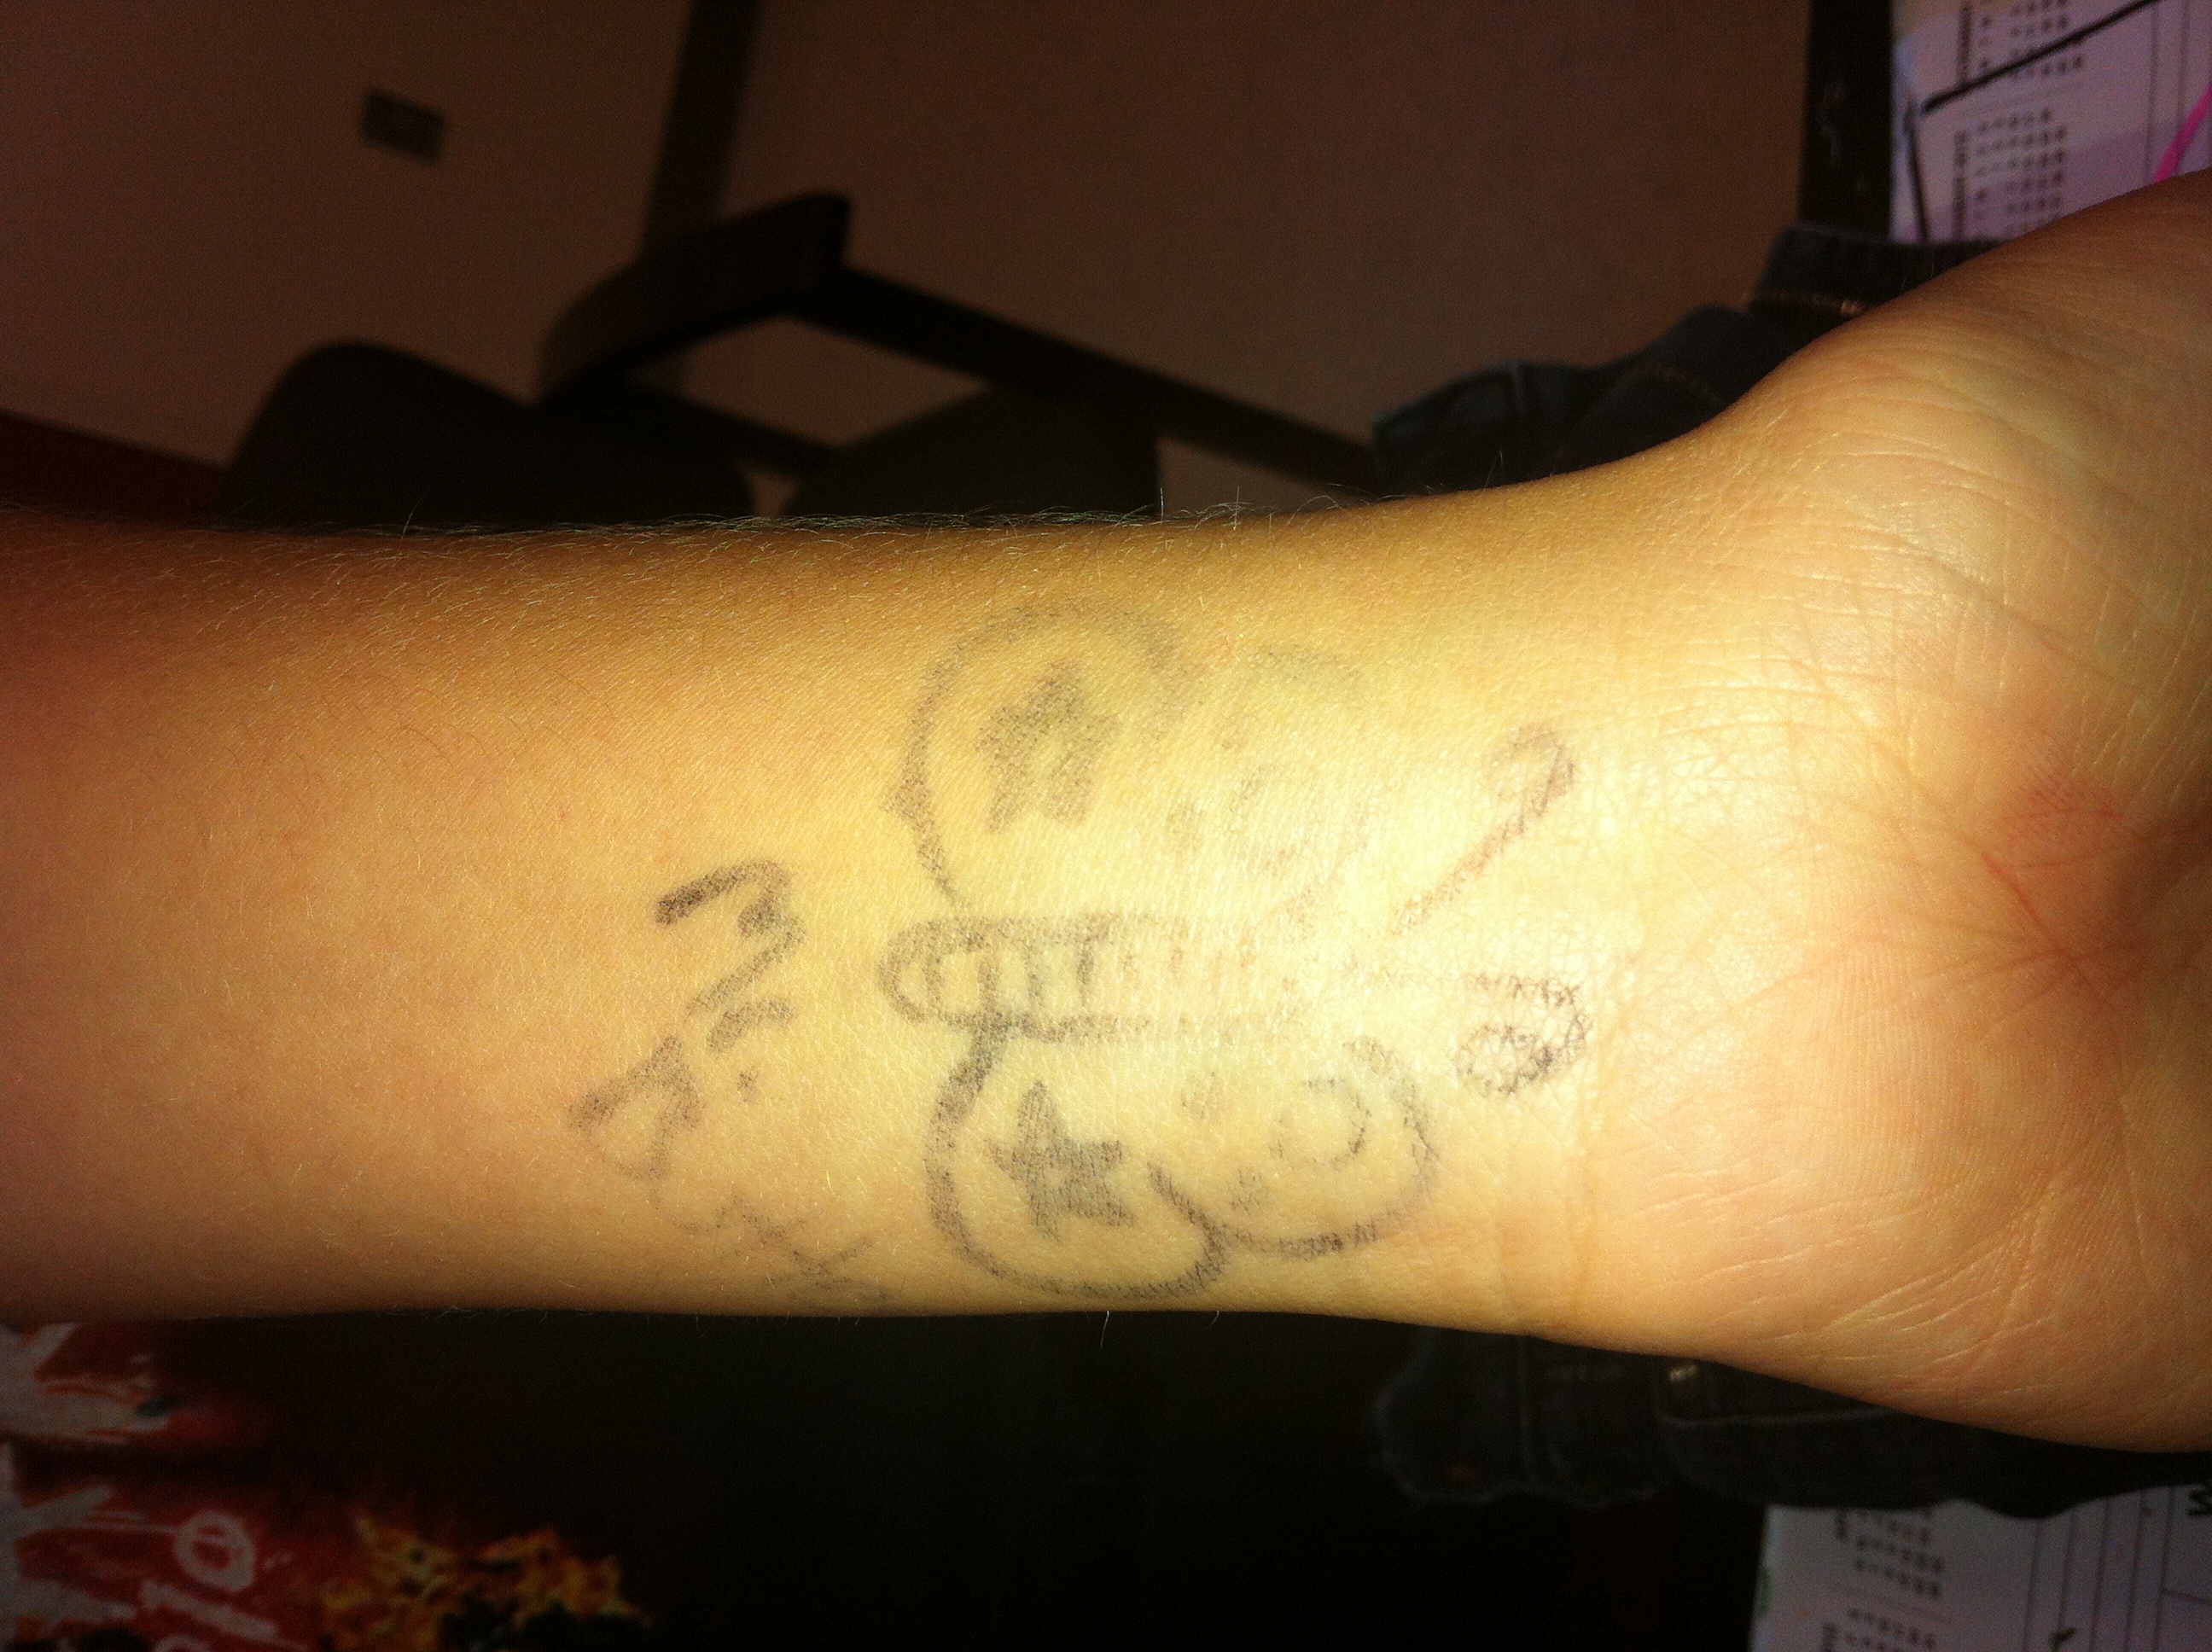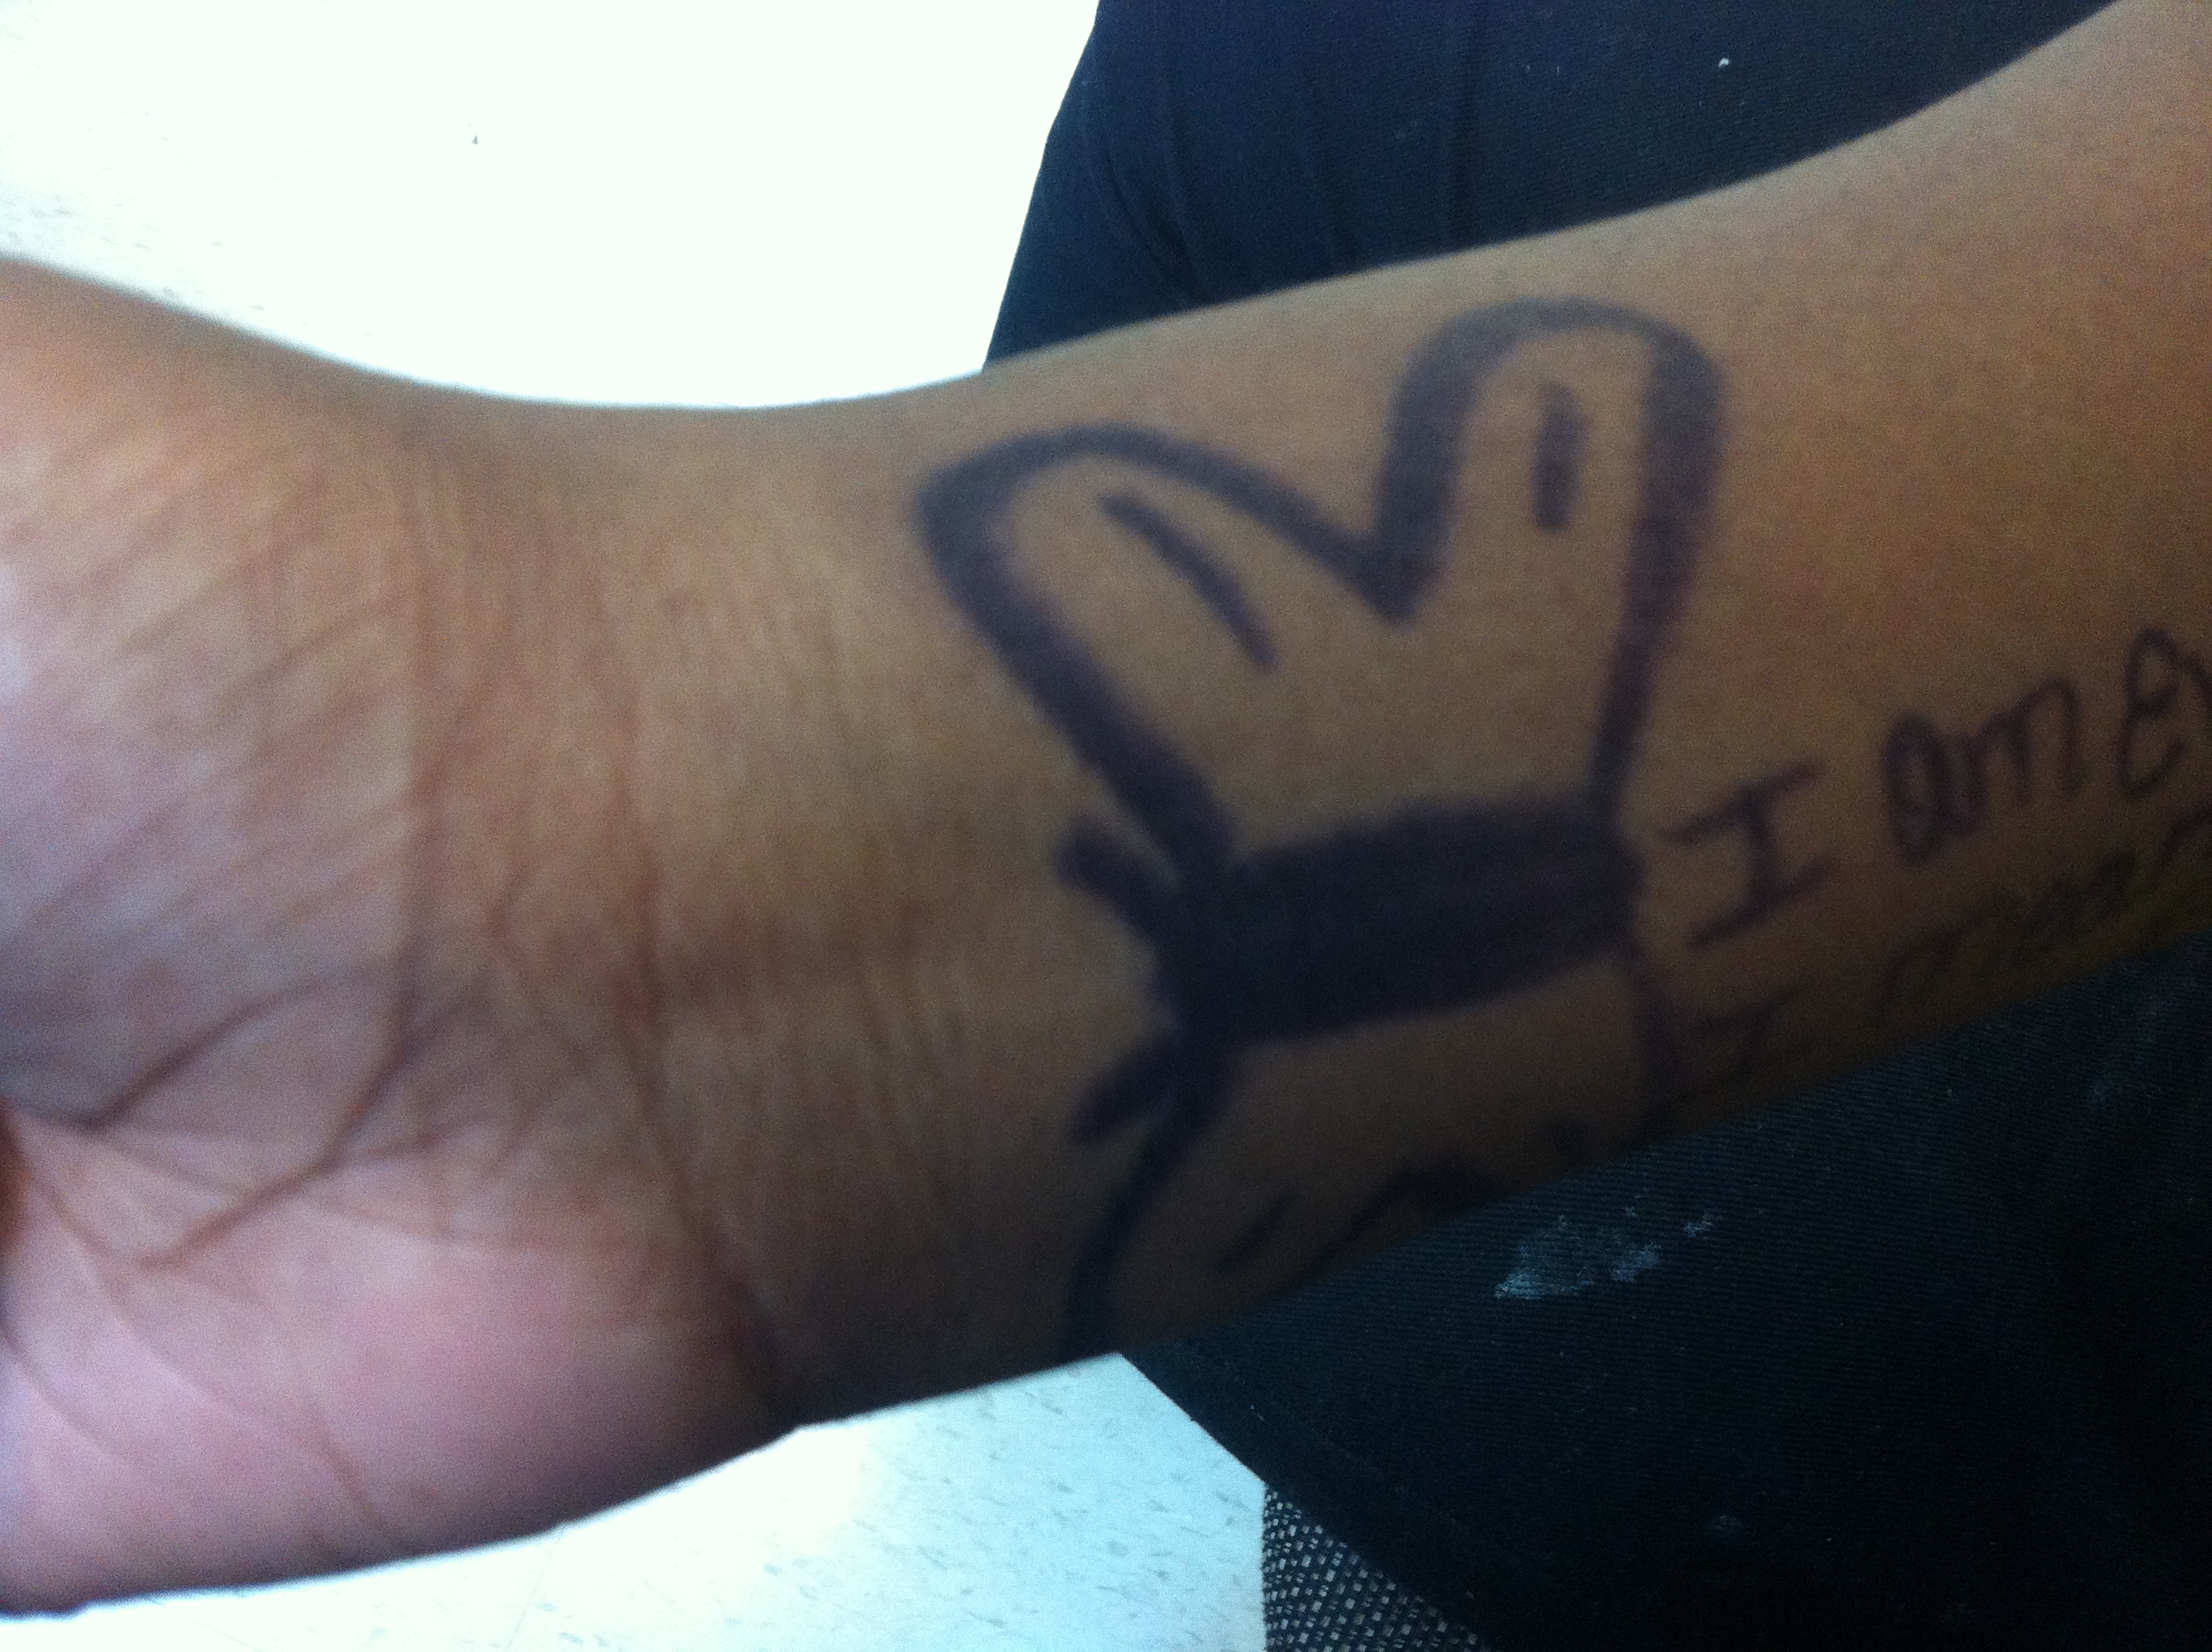Acting Out in School as a Way of Hiding a Learning Disability

There are variety of reasons kids act out in school, but they all usually act out to either hide something or as a way of expressing something they don’t know how to express in a more appropriate manner.

Earlier this week I sat in on an executive board meeting with various members of the Department of Juvenile Justice in the state of Florida and was reminded of Dexter Manley’s incredible story. 

Dexter Manley was an American professional football player who liked to give back to his inner-city community. Often he would go to various schools and speak to children about the importance of an education. Well one day after he had gotten through giving an inspiring speech to a group of elementary school kids, he was asked to read to them from an elementary level book. Dexter tried to get out of the situation, but he was cornered and eventually broke down crying. He had been hiding a secret that he was terrified would be exposed. He couldn’t read. Here was a man who had not only graduated from high school, but had also went to college and yet wasn’t able to read beyond a second grade reading level.

In elementary school Dexter realized in the second grade he had learning issues (poor auditory memory) and was often teased by other students. In return he started acting out in class, becoming a “troubled student” and even once pushed one of his teachers against the wall. He was passed on from class to class and grade to grade until he eventually graduated high school with only a second grade reading level. He had become a master at hiding his learning disability so well that he made it through college and much of his adult life without even his children and wife knowing he could barely read or write, but it all started in elementary school where he learned that acting out in class got him out of having to reveal that he was having trouble reading, writing or understanding material his peers were grasping. 

That got me to thinking about the many “troubled” teens I work with and I noticed before that most of them also had failing grades and very poor reading and writing skills, but I had been under the impression that it was mostly due to their lack of participation in class, lack of concentration, attention and motivation. It wasn’t until recently that I started realizing that many of them act out to hide the fact that they are suffering from one learning disability or the other. Now when I am referred a kid by a teacher or guidance counselor for “behavior issues” I also check their academics and their grades usually are very poor. Eventually I usually learn that their reading and writing skills are also extremely poor and I say “eventually” because it is usually hard to get them to write or read anything, they are usually master manipulators and will either change the subject, get angry or deviant. One kid in particular walked around with a stack of books, about five books checked out from the library in her arms at all times. I always thought she was an avid reader, but one day when I called her in my office and she came with her books, I asked her about each book and realized she hadn’t read any of them. When I tried to coach her into reading one to me, she struggled through a line or two and then became very angry and deviant. She stopped reading. She could barely read and she was a 17 year old high school junior.

Although I believe the practice of just passing troubled kids through school to get rid of them is less common today in the age of standardized testing, I am all too aware of many recent and not so recent high school graduates who read and write on elementary grade levels and seem to have slipped through the cracks of our educational system. Often times teachers send me kids they have kicked out of their class for “acting out”, and these kids are usually failing that class and have learned very quickly that if they act out, they will either get left alone or removed from the situation they don’t want to be in anyway. Up until recently, the real situation wasn’t getting dealt with as I had ignored the possible learning issues going on and went straight to trying to solve the cognitive and behavioral problems as I’ve been trained to do. 

Without help, these kids who manage to skate through high school will find that functioning in the real world is much harder. Many of the manipulation, distracting and defense mechanisms that worked in high school will not work in society and may actually get them hurt, arrested or worse. Unlike Dexter Manley who was a star football player and had the athletic talent and financial resources to hide his issues (at least for awhile), most of these young people will be unable to get or keep jobs and will most likely turn to drugs, alcohol, and criminal activities as ways of trying to cope. Ignoring the problem now will only cost everyone more later when these young people are carjacking us, or we are using our tax payers money to feed them in jail.  

If you have or are a parent of a child with a learning disability I would love to hear from you.

If you are a parent and have a child that is acting out and also struggling in school, it would be a good idea to have him or her tested for a learning disability. I think often learning disabilities go undiagnosed because parents are unwilling to have their kids tested. No one wants to have a child with a learning disability, but having that disability identified and attended to will allow that child to learn how to adjust and succeed. Not giving your child that opportunity out of fear of labeling could be detrimental to his/her future.

To read more about Dexter Manley you can click on this link http://findarticles.com/p/articles/mi_m1077/is_n12_v44/ai_8010811/?tag=content;col1

help4yourfamily's avatarhelp4yourfamily

Written by, Kate Oliver, MSW, LCSW-C

The day-to-day tasks that come with being a parent can make it difficult sometimes to stand back and see the forest for the trees.  With all the chauffering, making of meals, time keeping, study supporting, and the coaching/ disciplining we can get into a rut and forget something important… we forget about creative solutions.  Creative solutions are all around us.

I remember when my husband and I figured out that dates can happen during the day!  We decided that instead of going out in the evening when we are already tired and ready to crawl into bed, we would get the babysitter for the day.  That way we can go get lunch, when the restaurants are nearly empty, and see a movie or take a walk together, then come home and be there to put the girls to bed.  We enjoy each other so much when we are not tired.

Sometimes…

View original post 392 more words

The Symbiotic Relationship of Counseling and Unconditional Positive Regard

As another school year ends I look back at all the clients I’ve worked with during the school year and a good majority have made major changes. I’ve seen teens who could barely stay in school for a month because of getting suspended, end up having zero discipline issues for the last five months or more. I’ve seen kids with alcohol and marijuana problems minimize and some totally quit using and even more importantly I’ve seen kids I thought would take years to make positive gains make dramatic changes over a few months. 

I give all my clients surveys before discharging them so that they can voice how I have helped them or didn’t help them so that I could better myself in the future and this year I became emotional as I read over some of their responses. Some kids wrote things such as

  • “You helped me have a better relationship with my mother”
  • “You helped me realize that killing myself isn’t the answer”
  • “You helped me learn to love myself”
  • “You helped me learn how to get along with my baby’s father and take better care of my baby”
  • “I’ve learned to control my anger and how to express my emotions”
  • “You helped me learn how to get along with my baby’s mother and get more into my son’s life”
  • “You helped me realize how valuable my life is and how stupid and irresponsible ending it would be”
  • “I don’t smoke or drink any more and started liking myself”


This comments really touched me and made me feel blessed to have had such an impact on these kids and they have had major impacts on me as well. I’ve learned just as much about them about patience and the importance of bringing the family into counseling whenever possible and appropriate. I look back and try to reflect on all the things and activities I’ve done with these kids and while I’ve used a lot of counseling techniques, I think the one thing that made the biggest impact is the unconditional positive regard I’ve showed these kids. Unconditional positive regard is accepting someone as they are and not judging them and I showed these kids throughout the year that I liked and accepting them despite anything they did or said. Sure they often did things I didn’t approve of, but I always let them know that it was the act that I disapproved of and not them. A lot of these kids have never had anyone they could just talk to who accepted and didn’t judge them and I think building on that relationship overtime had the greatest impact.

A lot of times I hear interns and new counselors saying that they are afraid that they are afraid that they won’t always know what to say and I always tell them that it’s okay, sometimes I don’t know what to say and so I say nothing, I just listen and show unconditional positive regard and empathy instead of not being present in the situation because I am busy searching for the right thing to say when there likely isn’t. In a good counseling relationship it is symbiotic. I learn from them and they learn from me and that is one of the things I love best about being a counselor. I learn from even the most difficult of clients and hopefully they learn from me as well. 

Trying to Understand Teenagers Part I: Psychosocial Development

According to Erik Erikson’s theory of psychosocial development, during the ages of 12 to 18, teenagers are mostly focused on the questions “Who am I?” and “What do I believe and stand for?”

Identity versus confusion is thought to be the psychosocial crisis that teens are dealing with and many of us will probably agree that the teen years are full of trying out different roles and groups of friends to see where we fit in. This is natural and healthy as it helps us develop a sense of self, independence, a sense of belonging and a sense of individualism. If dealt with in an unhealthy way, this stage leads to feelings of confusion, and insecurity about themselves and where they fit into the world. At its worst it can lead to social and psychological impairments such as personality disorders, mood disorders, eating disorders and substance abuse.

Social relationships become the outmost important things to teenagers, which again is natural because humans are social beings and we need to learn how to get along with others and work together, but often times teens will put such great importance into their social relationships that everything else takes a back seat including familial relationships and academics. I see teens all the time whose biggest concern to them is their three month old relationship and not their failing grades and trying to get them to understand what should be important to them is more likely to give me gray hairs than it is to change thier point of view. Teens often sacrifice their relationship with parents to fulfill their needs for social relationships and usually don’t quite understand why we adults won’t just leave them alone to do what they want to do. A teenage girl I work with in individual and family counseling often cries to me that she just wants her mom to leave her alone and stop being worried about her. This young girl has been brought home at two in the morning by the police on a school night when her mom thought she was asleep, has been caught drinking and smoking marijuana and is failing school, yet she wants her mom to just let her “live my life”. This young girl is currently suspended from school after being caught having sexual contact with a boy in a restroom on campus.

It is natural for teens to try on different roles, friends, activities and behaviors to see what fits them and what doesn’t. This at times can be scary for those of us who watch the teens we know and love morph into and out of different roles and characters on their quest of finding their own identity and sense of direction.

With healthy and appropriate encouragement, reinforcement and support during this stage, teens will emerge with a strong sense of who they are, a feeling of independence, confidence and control over their lives. Those who come out of this stage unsure of who they are, what they want and what they believe are at a higher risk of developing the psychological impairments mentioned above as well as continue to feel insecure and confused about who they are into their adult years.

Teen Mom Wants to Have Another Baby ASAP

What if your 18 year old daughter who is in the 11th grade of high school, already has a two year old child, told you she was planning on having another child by her new boyfriend in order to not be selfish?

Working with teenagers it’s rarely anything I see or hear these days that shock me, however, there are plenty of things I see and hear that leave me dumbfounded, including when one of my favorite teenage clients, who already has a child, told me that she plans to stop taking her birth control so she can get pregnant by her new boyfriend of only about three months. What?!?!

She told me that she thought it was UNFAIR to her son that he didn’t have a sibling and unfair to her new boyfriend that she didn’t have a child by him and that she felt like she was being selfish to everyone by WAITING until the right time (oh, let’s say after she finished high school, started a career, got married) to have another child. I sat listening to her, almost hoping that I had falling off into a daydream and that this was just all part of my imagination, but it wasn’t. This high school junior, soon to be senior, with one child at home already was telling me that she was planning on getting pregnant again as soon as possible! She is already raising this child without the father’s involvement and I shouldn’t say she is raising her child because her parents are actually the ones taking care of her and her current child, yet she wants to go and get pregnant again!

I know part of the psychology of why she wants to get pregnant again is to keep her current boyfriend around. She is thinking that if she gets pregnant by her current beau, they will stay together forever. I am sure she had that same delusional fantasy with her current child’s father who she hasn’t seen in over two years. You would think she would have learned, but the delusional, fantasy world and mind of a teenager is a hard shell to crack, no matter how many times the world gets dropped on it.

As I listened to her, I actually felt a great deal of heartache for her because she was about to go and do something dumb… at least in my professional opinion. The chances of her being 18 with two kids, barely a high school degree, and being successful aren’t in her favor, especially coupled with her history of alcohol and drug use and her impulsive behavior that often leads her to be in dangerous situations.

I tried and hope I spoke some sense into her. I told her that she isn’t being selfish by waiting for the right time (and person) to have another child. I told her that it is OKAY for her to be selfish when it comes to her life. A lot of times we are told so many times about not being selfish that we forget that sometimes being selfish is a form of self-care and self-preservation. I also told her that it wouldn’t be fair to her, her current child or her future children if she once again got pregnant by a man who wouldn’t be around to help her raise the child(ren) they produced together. I definitely tried to convince her that waiting until after high school, after college (which she plans to attend), and hopefully after getting married, would be the time for her to have more children if she so chose to do that. Being a high school senior next year with two kids her and her parents are raising together is not the situation she wants to be in.

I really hope I convinced her that having a child right now, with a guy she’s only known for three months, is not a rational decision, but a large majority of the teenage mind functions irrationally. Their brains are just wired differently at this age and we’ll explore that in a future post. The bottom line is, every high school girl I’ve worked with that got pregnant to keep a boy NEVER ends up with that boy more than a year or so later. Does it happen? I’m sure it does, but I haven’t seen it. Still, it doesn’t stop them from thinking otherwise and even if they already had a child and that child’s father disappeared shortly after the birth of the child, some of them will still be convinced, as this young lady is, that it won’t happen again.

This isn’t the first time I had to deal with something similar to this. Not too long ago one of my high school clients who had a baby less than a year ago, wanted to have another baby right away because that is what her boyfriend (the babys’ father) wanted. A month or so later they broke up because he wasn’t helping her take care of the baby they already had. Imagine if she would have gotten pregnant with a second child like she wanted.

Not Catching the Ball: A Form of Self-Care

I’m not the first to say this. Matter of fact, I heard this from one of my mentors who is a successful therapist, but even before her, I can swear I might have heard it on Oprah or somewhere, but the fact remains it is a powerful statement that has helped me in many situations.

Often in life we get swamped with obligations that we’d rather not do. I don’t mean the things that we have to do like take care of our kids or pay the bills, but I mean things such as running an errand for a friend that would really inconvenience us, or dealing with someones emotional instability that we know will suck us of any energy we have, but we may feel obligated to listen, or help, or volunteer, or say “yes” when we really want to say “no”.

The thing is, these things asked of us by friends, family, neighbors, co-workers, or who ever, is like them throwing a ball to us and we often feel obligated to catch it, but we don’t have to. We can say no, we can politely turn down that invitation to a Christmas party we really don’t want to go to, quite simply, we can just let the ball pass or bounce on by us instead of feeling obligated to catch it.

I had to explain this to a client recently who gave a guy her number when she didn’t really want to, but didn’t know how to say no, and now when he calls she doesn’t really want to answer, but does so to not be rude. I had to tell her that just because he was throwing the ball to her, didn’t mean she had to catch it. The same goes for someone giving you a bad attitude, negative energy or whatever. Just because they throw that negative ball your way, you don’t have to catch it and throw it back, you can just let it pass on by you.

Many times we feel the need to, and sometimes out of habit (or reflex) catch balls we really shouldn’t and sometimes even throw them back. People will always throw balls at us and if we try to catch them all we’ll eventually end up dropping everything.

So I think it’s important from time to time to practice not catching the ball, which will allow us more time and energy for what we feel is most important to us.

Saving the Lives of Butterflies: Part 2

It’s been a few months since I first introduced The Butterfly Project to the high school kids I work with (if you haven’t already, you can check out my post entitled “Saving the Lives of Butterflies”). Well I’m happy to report that over the past two weeks I’ve had a number of them come up to me and show me the butterflies that they drew on themselves in efforts to refrain from cutting themselves! I was so happy to see one or two of them do this, but was overwhelmed to see nearly all of the ones who have issues with self-injury trying this technique and so far it appears to be helping! Some of them even name their butterflies and they have been encouraging each other. It’s a small step, but I am so thrilled by it’s success so far that I just had to share some of the pictures!

With summer coming up, I am really worried about all of the teens I work with at the high school, especially the ones who self-injure, but I am really hoping that everything I’ve taught them over the summer, including cognitive behavioral interventions, emotional self regulation strategies and now the Butterfly Project, will help them make it through whatever they encounter and that they will emerge stronger and more confident. I will also be worried about the ones who use drugs, the ones who make irrational decisions, the ones with anger issues and the ones with severe depression and anxiety. Pretty much, I’ll be worried about all of them, but I have to hope and trust that I’ve helped them all enough or at least did my part in preparing them to better handle life.

On Childhood Disintegrative Disorder


We conclude our discussion on the Pervasive Developmental Disorders with a brief overview of Childhood Disintegrative Disorder.

Introduction

Childhood Disintegrative Disorder (CDD), is also known as Heller’s Syndrome and Disintegrative Pschosis.  It is a rare Pervasive Developmental Disorder that affects about 1 in 100,000 children. CDD resembles many of the other disorders on the Autism spectrum in the fact that it involves developmental delays, impairment in communication and social functioning, but most closely resembles Rett syndrome in that it almost exclusively affects boys whereas Rett syndrome almost exclusively affects girls. New research suggest that while CDD affects boys more than girls at a rate of 4 to 1, it is thought that girls diagnosed with CDD most likely should have been diagnosed with Rett. There is also further talk that in the future Rett and possibly even CDD won’t be separate diagnosis, but that they will both be collapsed into the Autistic category as low functioning forms of Autism.

Symptoms

Children with CDD develop normally up until about ages 2 to 4 years of age (rarely there are cases of delayed onset up to 10 years of age), and then start regressing, losing previously acquired developmental skills with in a few months to years, including language, non-verbal communication skills, motor skills and social skills.

Symptoms include:

    • Delay or lack of spoken language
    • Impairment in nonverbal behaviors
    • Inability to start or maintain a conversation
    • Lack of play
    • Loss of bowel and bladder control
    • Loss of language or communication skills
    • Loss of motor skills
    • Loss of social skills
    • Problems forming relationships with other children and family members

Causes

There are no known causes of CDD although abnormal electroencephalograms (EEG), epilepsy, Lipid storage diseases (excess build up of toxic fats in the brain and nervous system), Tuberous sclerosis (benign tumors that may grow in the brain and other vital organs) and Subacute sclerosing panencephalitis (chronic infection of the brain due to a form of the measles that damage the brain) all appear to be associated with CDD.

Treatment

There is no cure for Childhood Disintegrative Disorder and the treatment for it is similar to the treatment for all of the Pervasive Developmental Disorders with the addition of trials with steroid medications to try to slow down the progress of the disorder.

Diagnosis

Physicians will use some of the same assessment tools used to diagnose the other Pervasive Developmental disorders with the inclusion of all the symptoms listed above and impairment in normal function or impairment in at least two of the following three areas:

  • Social interaction
  • Communication
  • Repetitive behavior & interest patterns

The main symptoms to look for in diagnosing CDD is the loss of previous learned skills in at least two of these areas:

  • Expressive language skills (being able to produce speech and communicate a message)
  • Receptive language skills (comprehension of language – listening and understanding what is communicated)
  • Social skills & self-care skills
  • Control over bowel and bladder
  • Play skills
  • Motor skills

If your child has any developmental delays or starts to lose developmental functions previously learned, it is vital to talk with your physician in order to rule out  CDD or any of the Pervasive Developmental Disorders or mental retardation. The faster any illness is discovered and treatment begins, even if there is no cure, the better the prognosis or at least the slowing of the progress of the disorder. Some children with similar, yet less severe symptoms may have a learning disability or something much less serious than a Pervasive Developmental Disorder, but it is important to have everything ruled out for the best care of your child.

Excellent post!

help4yourfamily's avatarhelp4yourfamily

Written by, Kate Oliver, MSW, LCSW-C

Get ready to laugh and tell me I’m wrong!  I have heard many versions of this affirmation but the person I got it from is the mother of affirmations herself, Louise Hay.  This week’s affirmation is:

Everything is happening at just the right time.

I know you do not believe me but give me a minute to talk you through it.  I know it feels like things happen too slow, too fast, or at just the wrong time!  This affirmation requires a little faith that there is a plan for us.  Even if you are not a believer in a higher power, doesn’t it just make life simpler to believe that everything is happening at just the right time?  I use this affirmation when I am running late and, I’m happy to tell you that when I use it, and believe it, everything does…

View original post 542 more words

On Rett Syndrome

An Introduction to Rett Syndrome

 What separates Rett syndrome from the other Pervasive Developmental Disorders is that it almost exclusively affects girls, whereas Autistic Disorder affects boys at a much higher rate than girls.

Worldwide Rett Syndrome affects 1 in every 10,000 to 15,000 females of all races and ethnicity. Prenatal testing is possible for families who have had a child born with Rett, but since the chances of developing Rett is so low, the chances of a family having two children born with Rett is less than 1%. Most boys born with the genes thought to be responsible for Rett often die shortly after birth. Because Rett syndrome is thought to be caused by a mutation to the X chromosome, girls are thought to be more able to compensate for the mutation because they have two X chromosomes where boys only have one and aren’t able to compensate.

In Rett Syndrome, similar to Asperger’s, there is normal early development and then a slowing of development, distinctive hand movements, lack of purposeful use of hands, and slowed head and brain growth. Problems walking, seizures and intellectual disability are usually also present. This disorder was first described by Dr. Andreas Rett, an Austrian physician in 1966, but it wasn’t until later in 1983 that it was recognized as a disorder after an article about it was written by Swedish researcher Dr. Bengt Hagbeg.

Like all of the Pervasive Developmental Disorders, the severity of symptoms in Rett varies from child to child, but they all start with relatively normal development, although loss of muscle tone (hypotonia), jerkiness in limb movements and difficulty feeding are often noticeable even in infancy. Gradually more apparent physical and mental symptoms become apparent such as the inability to talk and loss of purposefully movement of hands which is followed by compulsive hand movements such as wringing and washing.  Other symptoms such as problems walking, crawling and lack of eye contact may also be early signs. This period of regression is often sudden. The inability to perform motor functions (Apraxia) is one of the most severe disabilities of Rett syndrome, it effects body movement, eye gaze and speech.

Early stages of Rett syndrome often resemble Autistic disorder or one of the other Pervasive Developmental Disorders.  Some symptoms may also include walking on toes, awkward gait, difficulty chewing, teeth grinding, slowed growth, sleep problems, breathing problems, air swallowing, cognitive disabilities and apnea (holding breath)..

Diagnosis

Rett is typically diagnosed by a developmental pediatrician, pediatric neurologist or clinical neurologist using many of the same neurological, physical and psychological assessments used to diagnose the other Pervasive Developmental Disorders with the inclusion of genetic testing to look for the MECP2 mutation on the child’s X chromosome.

The Diagnostic and Statistical Manual of Mental Disorders also has these criteria for diagnosing Rett Disorder.

  • All of the following:
    • apparently normal prenatal and perinatal development
    • apparently normal psychomotor development through the first 5 months after birth
    • normal head circumference at birth
  • Onset of all of the following after the period of normal development:
    • deceleration of head growth between ages 5 and 48 months
    • loss of previously acquired purposeful hand skills between ages 5 and 30 months with the subsequent development of stereotyped hand movements (i.e., hand-wringing or hand washing)
    • loss of social engagement early in the course (although often social interaction develops later)
    • appearance of poorly coordinated gait or trunk movements
    • severely impaired expressive and receptive language development with severe psychomotor retardation

Causes

According to research, nearly all cases of Rett syndrome are due to a mutation in the metyl CpG binding protein 2 (MECP2) gene. The gene was discovered in 1999 and controls many other genes. It may also be responsible for some of the other Pervasive Developmental Disorders. This gene is needed for brain development and helps other genes increase or decrease their own unique expressions and proteins. This genes malfunction causes other genes to become abnormal. The puzzling thing is, not everyone with MECP2 mutation has Rett syndrome, so other genetic mutations are also thought to be responsible and research is ongoing. Rett syndrome is not thought to be genetic. Only about 1% of Rett syndrome cases are thought to be inherited, which means that in the overwhelming majority of cases, the gene mutations are random.

Treatment

Just like all the other Pervasive Developmental Disorders, there is no cure for Rett Syndrome and treatment is pretty similar including medication and therapy to help control and minimize many of the disabling features of Rett syndrome.

Although Rett syndrome can be very disabling, many people with Rett live to be in their 40’s and 50’s and perhaps even longer . 

Resources

International Rett Syndrome Foundation: www.rettsyndrome.org

National Institute of Child Health and Human Development (NICHD): www.nichd.nih.gov

Office of Rare Diseases: www.rarediseases.info.nih.gov

Rett Syndrome Research Trust: www.rsrt.org